INTRODUCTION
Seborrheic dermatitis (SD) is a chronic, relapsing inflammatory condition. SD affects areas that are rich in sebaceous glands, most commonly the scalp (SSD).1 In adults, SD occurs in approximately 1-3% of the general population, affecting men more often than women.2 There is a spectrum of disease in SD that ranges from mild to severe.3 Mild cases are sometimes referred to as dandruff or pityriasis sicca. This form of SD is characterized by dry flaking, often likened to snowflakes, which is noticeable on the scalp, hair shafts, and clothing. In more severe cases of SD, the inflammation may be more clinically evident with thick, greasy, yellowish flakes adherent to an erythematous scalp. The face is the second most affected area with similar appearing patches located symmetrically on the central face, nasolabial folds, alar creases, and eyebrows. SD can also affect the ear canals, post-auricular area, neck creases, central chest, axillae, and inguinal folds. In melanin-rich skin, pink or hypopigmented annular coalescing ring-like scaling lesions, referred to as Petaloid SD, may be seen in and along the hairline and on the central face.4 The primary symptom associated with all forms of SD is intense itching, although some patients note burning, stinging, and/or cosmetic product intolerance.5 The burden of SD is significant, with sufferers experiencing not only physical signs and symptoms, but the embarrassment associated with unsightly visible flaking that can affect self-esteem.
The pathogenesis of SD is complex, and our understanding is still evolving. There appears to be an interplay between microbial colonization, altered lipid composition, and epidermal barrier dysfunction. In SD, there is an increased abundance of Malassezia spp. on the scalp that is related to disease
appearance and severity.6 Malassezia are lipophilic commensal yeast that thrive in sebum-rich skin.7 They secrete lipases that hydrolyze sebum triglycerides into saturated and unsaturated free fatty acids.8 The saturated fatty acids serve as a nutrient source for Malassezia, while the unsaturated fatty acids, such as oleic acid and arachidonic acid, accumulate on the skin surface.9 These unsaturated fatty acids are pro-inflammatory and impair barrier function. In addition, Malassezia restricta has been shown to oxidize squalene to squalene peroxides that increase oxidative stress, trigger inflammation, and alter epidermal proteins.10 These altered proteins impair barrier function and cause flaking. Scalp affected by SD also shows an alteration in intercellular barrier lipids, including a change in the composition of ceramides that correlates with barrier dysfunction.11 Environmental and genetic factors can be linked to SD.12 Diet, physical and emotional stress, hormones, alcohol consumption, and smoking may play a role.13 Pollutants can affect the severity and occurrence of dandruff, and flare-ups are more prevalent under conditions that favor the growth of Malassezia spp. including cooler temperatures, low humidity, and lower UV exposure.14
The treatment of SD includes a selection of anti-fungal agents to control Malassezia spp., anti-inflammatory compounds, and keratolytics to facilitate the removal of flakes.15,16 Ketoconazole is a commonly used agent that is fungistatic against Malassezia spp. and has been shown to lower the load of Malassezia spp. and improve signs and symptoms of SD.17 Studies have confirmed that both 1% and 2% ketoconazole shampoo are effective for treating dandruff and SD.18 Selenium disulfide is an effective anti-dandruff ingredient that is fungicidal to Malessezia spp, rebalances the bacterial composition of the scalp, and has keratolytic effects.19,20 Previous studies demonstrate that a 1% SeS2 shampoo is as effective as 2% ketoconazole shampoo for treating patients with moderate to severe SSD.21
In this study, 0.6% micronized selenium disulfide shampoo (SeS2) (Dercos® anti-dandruff US, Vichy Laboratoires, France) was compared to 2% ketoconazole (Nizoral™ 20 mg/g shampoo, Janssen Pharmaceutica, Belgium NV) for the treatment of moderate to severe SSD. In addition to SeS2, this shampoo includes ingredients to promote the removal of flakes, facilitate barrier repair, hydrate, and soothe the scalp.
MATERIALS AND METHODS
All subjects provided written informed consent, and the study complied with local legal regulations, good clinical practices, and the principles of the Declaration of Helsinki.
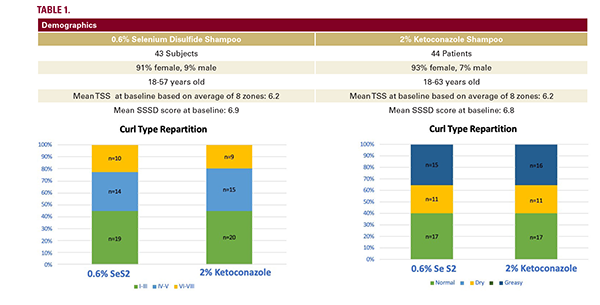
This study was a single-center, 6-week, randomized, doubleblind study with 2 parallel groups to compare the benefits and attributes of 2 shampoos on subjects with moderate to severe scalp seborrheic dermatitis. Subjects included men and women with Fitzpatrick skin phototypes III-VI, aged 18-63. Subjects were randomized into 3 sub-groups based on curl type: types I-III, IV-V, VI-VIII. While 8 curl types are defined by this classification, only types II-VII were represented in the study population.22 Scalp types included dry, normal, and oily. Each curl type and scalp type had a minimum of 2 subjects participating in each product category. A total of 87 patients were enrolled and completed the study. There were 43 subjects in the SeS2 shampoo group (91% female) and 44 subjects in the ketoconazole shampoo group (93% female; Table 1).
To be included, subjects had to have moderate to severe scales at baseline as determined by the Total Scales Score (TSS). TSS is the sum of adherent and non-adherent scales, with 0=no scales and 5=very large quantity of scales. TSS had to be greater than or equal to 4 (ranging from 0 to 10) at baseline with an adherent scales score greater than or equal to 2.5 (ranging from 0 to 5) and no limit for non-adherent scales score. The TSS was calculated by taking an average of 8 scalp zones. Subjects were instructed not to use any haircare products, including conditioner, hair masks, non-rinsed hair care products, oil, or anti-scale products for the duration of the study. Styling products were permitted but not within 3 days prior to a study visit, and hair color or bleach could be used, but not within a week of a study visit.
Subjects were excluded if they had used topical or oral corticosteroids, antihistamines, oral or topical anti-fungal medications, non-steroidal anti-inflammatory medications, immunosuppressives, or lithium-based drugs within 4 weeks before entering the study. Oral or topical retinoids could not be used for 6 months prior to the study. Patients with immunosuppressive disorders, severe medical conditions, or those who were pregnant or breastfeeding were excluded. Subjects with alopecia at the vertex (stage > IIIa Hamilton and > I Ludwig) or who had over 60% gray hair were excluded, as these phenotypes could obscure the ability to assess scales.
There was a 2-week washout period where subjects used a specified neutral, non-medicated shampoo three times weekly. On day 0, subjects were randomized to use either micronized SeS2 shampoo 3 times weekly or ketoconazole shampoo 2 times weekly. The frequency and method of product use were selected in compliance with the package instructions for both products. SeS2 shampoo users were directed to wet their hair, then massage the shampoo into the scalp to form a lather. After rinsing, they repeated the application, let it sit for 2 minutes, and rinsed thoroughly again. Ketoconazole shampoo was applied to the hair and scalp, left on for 5-10 minutes, then rinsed.
The investigator evaluated subjects on day -14, 0, 14, and 42. Total Scale Score (TSS) was determined at all time points, including day -14, and Symptomatic Scale of Seborrheic Dermatitis (SSSD) was assessed on days 0,14 and 42. The SSSD consists of 3 components, including erythema, scales, and pruritus. For each component, the severity ranged from 0 to 5, 0 being the absence of the signs/symptoms and 5 being the most severe form. The SSSD score is the sum of individual scores observed on each component, with a range of 0-15. A mild SSSD score was 0-6, moderate 7-9, and severe 10-15. Clinical assessment of pruritus, as reported by subjects, was conducted at baseline, day 14, and on day 42 with 0=no itching and 5=severe. On day 42, the investigator rated global product satisfaction on a 3-point scale (0=not satisfied and 2=very satisfied) and global efficacy on a 5-point scale (1=worst to 5=complete resolution or complete remission). Standardized photographs of the most affected zone were taken using Leviacam at all visits.
The cutaneous acceptability/tolerability evaluation consisted of two complementary phases: the first analyzed the relevant manifestations reported by the subjects in daily logs, and the second analyzed the relevant clinical manifestations observed by the investigator through cutaneous examination. Subjects rated the severity of discomfort (itching, burning, stinging, pruritus) at each visit. A questionnaire concerning efficacy/ product satisfaction, tolerability, and cosmesis/acceptability was answered by subjects at all visits. Evaluation of QoL was done using the Scalpdex questionnaire, which consisted of 23 questions that were answered at all time points.23 These questions were divided into 3 categories, including functioning, emotions, and symptoms, and a total QoL score was calculated.
For each parameter and timepoint, the evolution across time with respect to the baseline for each treatment group separately was investigated by using the Student’s Paired t-test. For each parameter, treatment group comparison, at each time point, was investigated, on the difference data with respect to baseline using the Student’s t-test for independent data. For parameters where no baseline values are present, the analysis was conducted on the values observed at the specific timepoints, and not on the difference data. P-value of < 0.05 was considered significant.
RESULTS
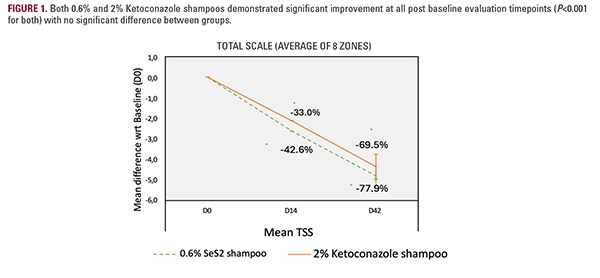
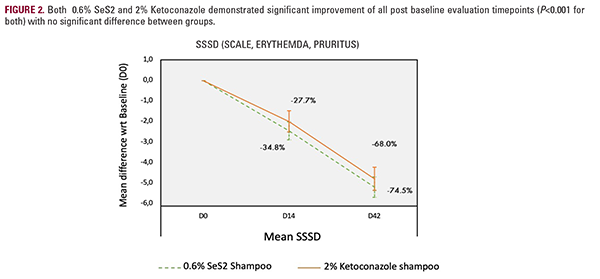
Table 1 presents the subjects' demographics and baseline assessment. Mean TSS score at baseline, based on the average of 8 zones on the scalp, was 6.2 in both groups. TSS improved with both shampoos over the course of the study, as seen in Figure 1. By day 14, TSS decreased 33.0% in the ketoconazole group and 42.6% in the SeS2 shampoo group (both P<0.001). On day 42, TSS decreased 69.5% with ketoconazole and 77.9% with SeS2 (both P<0.001). There was no significant difference between groups at any time point. At baseline, average SSSD scores across 8 scalp zones were 6.8 in the ketoconazole group and 6.9 in the SeS2 group. Mean SSSD improved at all post-baseline time points after using both shampoos, as seen in Figure 2. By day 14, SSSD decreased by 27.7% and 34.8%, and on day 42 by 68.0% and 74.5% with ketoconazole and SeS2, respectively (all P<0.001). There was no significant difference between the groups at any time point. The severity of all moderate cases improved to mild in both groups. This was also true for one subject with a severe SSSD score at baseline within the ketoconazole shampoo group. Both products show relatively similar evolution over all periods of evaluation, and the micronized SeS2 shampoo was found to be as effective as the ketoconazole shampoo at D14 and D42.
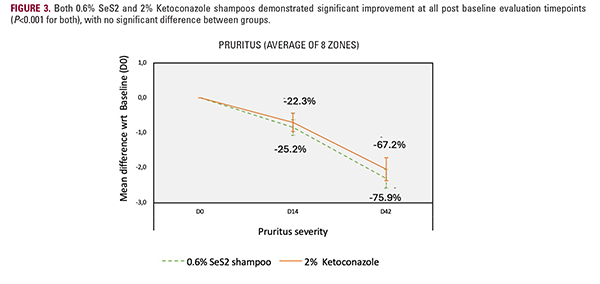
After product application, a significant improvement in the mean 'pruritus severity' score was observed for the average
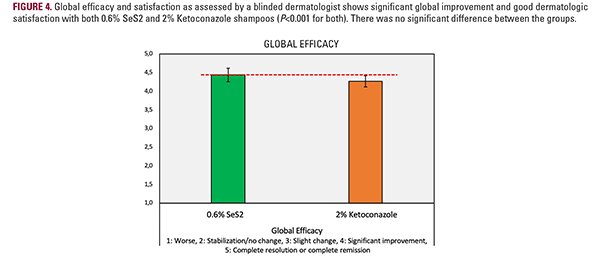
of 8 zones for both treatments across all time points. On day 42, pruritus decreased by 67.2% and 75.9% in the ketoconazole and SeS2 groups, respectively (both P<0.001; Figure 3). Product comparison revealed no significant difference between the two groups. Global efficacy and satisfaction, as assessed by the blinded dermatologist, showed significant improvement and good satisfaction with both test products (Figure 4).
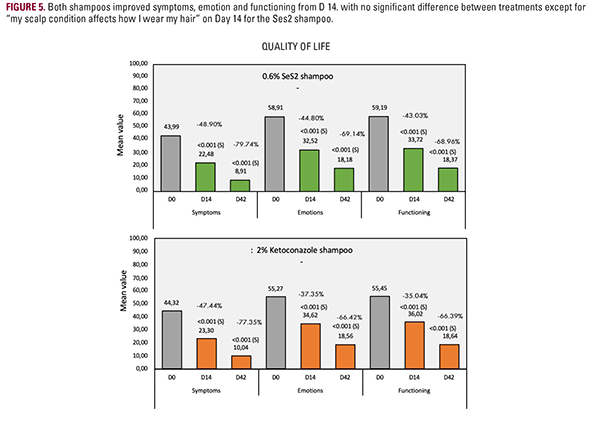
Subject self-assessment showed itching improved by 76.3% with ketoconazole shampoo and 81% with SeS2 shampoo by day 42 (both P<0.001), with no significant difference between groups. Quality of life improved as early as day 14, and on day 42, there was a 67.5% and 70.1% improvement after using the ketoconazole and SeS2 shampoos, respectively (both P<0.001; Figure 5). There was no significant difference between treatment groups except "my scalp condition affects the way I wear my hair" on day 14 for the SeS2 shampoo.
Investigator and subject assessment revealed excellent tolerability with no local discomfort or irritation from either test product. On day 42, overall satisfaction reported by study subjects was 97.7% and 100% for the ketoconazole and SeS2 shampoos, respectively (both P<0.001). A subject representing average improvement after using the SeS2 shampoo is seen in Figure 6.
In terms of cosmesis, there was a preference by subjects for the micronized SeS2 shampoo in terms of leaving hair soft, glossy, supple, natural appearing, and that the shampoo was suitable for their hair type. In the SeS2 and ketoconazole groups, respectively, leaves hair soft 98% vs 86%, leaves hair glossy 91% vs 78%, leaves hair supple 95% vs 82%, leaves hair natural appearing 100% vs 91%, and the product is suitable for my hair type 100% vs 87% (all P<0.001).

DISCUSSION
Patients with seborrheic dermatitis have a plethora of over-the-counter options from which to choose, including shampoos and leave-in treatments. A common complaint in the dermatologist's office is that although dandruff treatments are generally effective, many leave hair feeling dry, brittle, and less manageable; this is particularly true of shampoos. In this study, 0.6% SeS2 shampoo was found to be as effective as 2% ketoconazole shampoo for treating moderate to severe SD. In contrast, study subjects found that the micronized SeS2 shampoo was superior in terms of hair quality and appearance when compared to the ketoconazole shampoo. More subjects felt the SeS2 shampoo left hair soft, glossy, supple, natural appearing, and was suitable for their hair type when compared to the ketoconazole shampoo. Importantly, the SeS2 shampoo was preferred for its cosmetic benefits across curl types. This favorability is an important differentiator that may result in better compliance and improved treatment outcomes.
The efficacy and cosmesis of this SeS2 shampoo can be attributed to its unique formulation. SeS2 itself is a multitasking ingredient for treating SSD.24 It acts to rebalance the scalp microbiome, reducing Malassezia spp. and decreasing Staphylococcus epidermidis in favor of Cutibacterium acnes.19 SeS2 is cytostatic to the epidermis and reduces epidermal cell turnover, corneocyte production, and flaking.23 In a comparative study of anti-dandruff shampoos, SeS2 shampoo was found to have the highest keratolytic activity compared to formulations containing zinc pyrithione and ketoconazole.24 This SeS2 shampoo also contains salicylic acid (SA), providing additional keratolytic effects.25 SA is lipophilic and readily penetrates the stratum corneum, where it can help dissolve intercellular lipids between corneocytes, helping to loosen scales.26 SA also has anti-inflammatory activity and may help reduce irritation and mitigate the itch associated with SSD.27 Niacinamide, or vitamin B3, is an important cosmetic ingredient with diverse skin benefits.28 It is known to increase ceramide production and strengthen barrier function. Niacinamide reduces oxidative stress, mitigates inflammation, and may improve overall scalp health.28,29 Glycerin is a potent humectant, helping to moisturize the hair and scalp.30 Menthol provides a soothing and cooling effect that can reduce inflammation and facilitate healing.31,32 Thus, this micronized SeS2 shampoo contains carefully curated ingredients to provide a multi-modal approach to treating SSD.
CONCLUSION
In this study, 0.6% micronized selenium disulfide shampoo was found to reduce the signs and symptoms of moderate to severe scalp seborrheic dermatitis as effectively as 2% ketoconazole shampoo. The SeS2 shampoo was extremely well tolerated and provided superior cosmesis when compared to the ketoconazole shampoo, according to study participants across diverse curl types. The data presented here suggest that this micronized 0.6% SeS2 shampoo should be considered as an alternative to ketoconazole shampoo when treating patients with moderate to severe forms of SSD.
DISCLOSURES
This study was supported by Vichy Laboratoires. PF, VB, and
EH served as members of the Vichy medical advisory board for
this publication, and PF provided medical writing services for
this manuscript. NK is an employee of Vichy Laboratoires. All
authors contributed to the manuscript, reviewed it, and agreed
with its contents.
REFERENCES
- Elewski BE. Clinical diagnosis of common scalp disorders. J Investig Dermatol Symp Proc. 2005;10(3):190-193. doi:10.1111/j.1087-0024.2005.10103.x
- Ashbee HR, Evans EG. Immunology of diseases associated with Malassezia species. Clin Microbiol Rev. 2002;15(1):21-57. doi:10.1128/CMR.15.1.21-57.2002
- Cheng Y, Cong J, Xu J, et al. Research progress on the exacerbation of lipid metabolism by Malassezia and its impact on the skin barrier function. Cosmetics. 2025;12(2):67. doi:10.3390/cosmetics12020067
- Wu T, Frommeyer TC, Rohan CA, Travers JB. Uncommon petaloid form of seborrheic dermatitis seen in Fitzpatrick skin types V-VI. J Clin Investig Dermatol. 2023;11(1):10.13188/2373-1044.1000086. doi:10.13188/2373-1044.1000086
- Araya M, Kulthanan K, Jiamton S. Clinical characteristics and quality of life of seborrheic dermatitis patients in a tropical country. Indian J Dermatol. 2015;60(5):519. doi:10.4103/0019-5154.164410
- McGinley KJ, Leyden JJ, Marples RR, Path MR, Kligman AM. Quantitative microbiology of the scalp in non-dandruff, dandruff, and seborrheic dermatitis. J Invest Dermatol. 1975;64(6):401-405.
- Ro BI, Dawson TL. The role of sebaceous gland activity and scalp microfloral metabolism in the etiology of seborrheic dermatitis and dandruff. J Investig Dermatol Symp Proc. 2005;10(3):194-197. doi:10.1111/j.1087-0024.2005.10104.x
- Park M, Park S, Jung WH. Skin commensal fungus Malassezia and its lipases. J Microbiol Biotechnol. 2021;31(5):637-644. doi:10.4014/jmb.2012.12048
- Borda LJ, Wikramanayake TC. Seborrheic dermatitis and dandruff: a comprehensive review. J Clin Investig Dermatol. 2015;3(2):10.13188/2373-1044.1000019. doi:10.13188/2373-1044.1000019
- Jourdain R, Moga A, Vingler P, et al. Exploration of scalp surface lipids reveals squalene peroxide as a potential actor in dandruff condition. Arch Dermatol Res. 2016;308(3):153- 163. doi:10.1007/s00403-016-1623-1
- Rousel J, Nădăban A, Saghari M, et al. Lesional skin of seborrheic dermatitis patients is characterized by skin barrier dysfunction and correlating alterations in the stratum corneum ceramide composition. Exp Dermatol. 2024;33(1):e14952. doi:10.1111/ exd.14952
- Leroy AK, Almeida RF, Obadia DL, et al. Scalp seborrheic dermatitis: what we know so far. Skin Appendage Disord. 2023;9(3):160-164. doi:10.1159/000528738
- Woolhiser E, Keime N, Patel A, et al. Nutrition, obesity, and seborrheic dermatitis: systematic review. JMIR Dermatol. 2024;7:e50143. doi:10.2196/50143
- Akbulut TO, Suslu H, Atci T. Is the frequency of seborrheic dermatitis related to climate parameters? Sisli Etfal Hastan Tip Bul. 2022;56(1):91-95. doi:10.14744/SEMB.2021.67503
- Cheong WK, Young CK, Toresakar RG, et al. Treatment of seborrheic dermatitis in Asia: a consensus guide. Skin Appendage Disord. 2016;1(4):187-196. doi:10.1159/000444682
- Borda LJ, Perper M, Keri JE. Treatment of seborrheic dermatitis: a comprehensive review. J Dermatolog Treat. 2019;30(2):158-169. doi:10.1080/09546634.2018.1473554
- Tynes BE, Johnson CD, Vaish MH, et al. Ketoconazole shampoo for seborrheic dermatitis of the scalp: a narrative review. Cureus. 2024;16(8):e67532. doi:10.7759/cureus.67532
- Pierard-Franchimont C, Pierard GE, Arrese JE, De Doncker P. Effect of ketoconazole 1% and 2% shampoos on severe dandruff and seborrhoeic dermatitis: clinical, squamometric and mycological assessments. Dermatology. 2001;202(2):171-176. doi:10.1159/000051628
- Leong C, Schmid B, Buttafuoco A, Glatz M, Bosshard PP. In vitro efficacy of antifungal agents alone and in shampoo formulation against dandruff-associated Malassezia spp. and Staphylococcus spp. Int J Cosmet Sci. 2019;41(3):221-227. doi:10.1111/ics.12525
- Cohen PR, Anderson CA. Topical selenium sulfide for the treatment of hyperkeratosis. Dermatol Ther (Heidelb). 2018;8(4):639-646. doi:10.1007/s13555-018-0259-9
- Barbosa V, Melo DF, Vañó-Galván S, et al. A comparative randomized clinical study assessing the efficacy of a 1% selenium disulfide-based shampoo versus 2% ketoconazole shampoo in subjects with moderate to severe scalp seborrheic dermatitis. Skin Appendage Disord. 2024;10(6):497-504. doi:10.1159/000539209
- De la Mettrie R, Saint-Léger D, Loussouarn G, Garcel A, Porter C, Langaney A. Shape variability and classification of human hair: a worldwide approach. Hum Biol. 2007;79(3):265-281. doi:10.1353/hub.2007.0045
- Chen SC, Yeung J, Chren MM. Scalpdex: a quality-of-life instrument for scalp dermatitis. Arch Dermatol. 2002;138(6):803-807. doi:10.1001/archderm.138.6.803
- Barve SS, Deshpande S, Dhawal PP. Cytotoxic, cytostatic, and keratolytic activity of anti-dandruff shampoo formulations. Int J Res Dermatol. 2023;9(2):61-66. doi:10.18203/ issn.2455-4529.IntJResDermatol. 20230036
- Del Rosso J. Pharmacotherapy update: current therapies and research for common dermatologic conditions: the many roles of topical salicylic acid. Skin Aging. 2005;13:38- 42.
- Arif T. Salicylic acid as a peeling agent: a comprehensive review. Clin Cosmet Investig Dermatol. 2015;8:455-461. doi:10.2147/CCID.S84765
- Weirich EG, Longauer JK, Kirkwood AH. Dermatopharmacology of salicylic acid. III. Topical contra-inflammatory effect of salicylic acid and other drugs in animal experiments. Dermatologica. 1976;152(2):87-99.
- Berson D, Osborne R, Oblong J, et al. Niacinamide: a topical vitamin with wide-ranging skin appearance benefits. In: Farris PK, ed. Cosmeceuticals and Cosmetic Practice. John Wiley & Sons Ltd; 2014:103-112.
- Aydin F. Niacinamide improves scalp health and hair growth. Hair Ther Transplant. 2023;13(1):225.
- Chen HJ, Lee PY, Chen CY, et al. Moisture retention of glycerin solutions with various concentrations: a comparative study. Sci Rep. 2022;12(1):10232. doi:10.1038/s41598- 022-13452-2
- Li Z, Zhang H, Wang Y, et al. The distinctive role of menthol in pain and analgesia: mechanisms, practices, and advances. Front Mol Neurosci. 2022;15:1006908. doi:10.3389/fnmol.2022.1006908
- Rozza AL, Beserra FP, Vieira AJ, et al. The use of menthol in skin wound healing— anti-inflammatory potential, antioxidant defense system stimulation, and increased epithelialization. Pharmaceutics. 2021;13(11):1902. doi:10.3390/pharmaceutics13111902
AUTHOR CORRESPONDENCE
Patricia K. Farris MD [email protected]